Category: Medicine
China’s Medicines are Saving American Lives
The Economist reports that China is now the second largest producer of new pharmaceuticals, after the United States.
China has long been known for churning out generic drugs, supplying raw ingredients and managing clinical trials for the pharmaceutical world. But its drugmakers are now also at the cutting edge, producing innovative medicines that are cheaper than the ones they compete with.
… In September last year an experimental drug did what none had done before. In late-stage trials for non-small cell lung cancer, it nearly doubled the time patients lived without the disease getting worse—to 11.1 months, compared with 5.8 months for Keytruda. The results were stunning. So too was the nationality of the biotech company behind them. Akeso is Chinese.
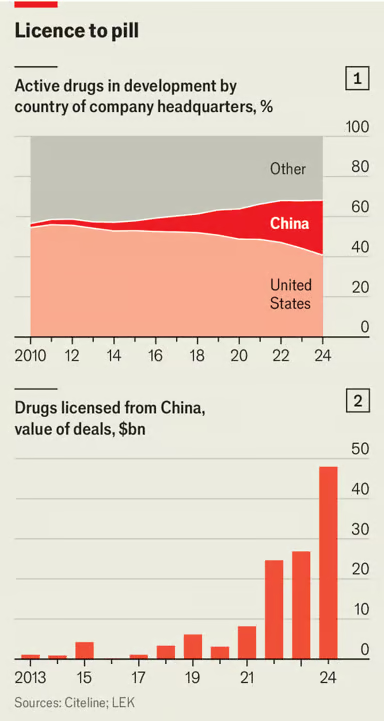
This is exactly what I predicted in my TED talk and it’s great news! As I said then:
Ideas have this amazing property. Thomas Jefferson said “He who receives an idea from me receives instruction himself, without lessening mine. As he who lights his candle at mine receives light without darkening me.”
Now think about the following: if China and India were as rich as the United States is today, the market for cancer drugs would be eight times larger than it is now. Now we are not there yet, but it is happening. As other countries become richer the demand for these pharmaceuticals is going to increase tremendously. And that means an increase incentive to do research and development, which benefits everyone in the world. Larger markets increase the incentive to produce all kinds of ideas, whether it’s software, whether it’s a computer chip, whether it’s a new design.
Well if larger markets increase the incentive to produce new ideas, how do we maximize that incentive?
It’s by having one world market, by globalizing the world. Ideas are meant to be shared.
One idea, one world, one market.
Sadly, some of us are losing sight of the immense benefits of a global market. Another example of the great forgetting.
As Girard predicted, China’s growing similarity to the U.S. has fueled conflict and rivalry. But if managed properly, rivalry can be positive-sum. A rich China benefits us far more than a poor China—including by creating new cancer medicines that save American lives.
Hat tip: Cremieux.
My excellent Conversation with Ezra Klein
Ezra is getting plenty of coverage for his very good and very on the mark new book with Derek Thompson, Abundance. So far it is a huge hit after only a few days. I figured this conversation would be most interesting, and add the most value, if I tried to push him further from a libertarian point of view (a sign of respect of course). Here is the audio, video, and transcript. Here is part of the episode summary:
In this conversation, Ezra and Tyler discuss how the abundance agenda interacts with political polarization, whether it’s is an elite-driven movement, where Ezra favors NIMBYism, the geographic distribution of US cities, an abundance-driven approach to health care, what to do about fertility decline, how the U.S. federal government might prepare for AGI, whether mass layoffs in government are justified, Ezra’s recommended travel destinations, and more.
Lots of good back and forth, here is one excerpt:
COWEN: Here’s a question from a reader, and I’m paraphrasing. “I can see why you would favor Obamacare and an abundance agenda because Obamacare throws a lot more resources at the healthcare sector in some ways. It did have Medicare cuts, but nonetheless, it’s not choking the sector. But if you favor an abundance agenda, can you then possibly favor single-payer health insurance through the government, which does tend to choke resources and stifle innovation?”
KLEIN: I think it would depend on how you did the single-payer healthcare. Here, we should talk about — because it’s referenced glancingly in the book in a place where you and I differ — but the supervillain view that I hold and your view, which is that you should negotiate drug prices. I’ve always thought on that because I think in some ways, it’s a better toy example than single payer versus Obamacare.
I think you want to take the amount of innovation you’re getting very, very, very seriously. I’ve written pieces about this, that I think if you’re going to do Medicare drug pricing at any kind of significant level, you want to be pairing that with a pretty significant agenda to make drug discovery much easier, to make testing much easier.
And:
COWEN: What should the US federal government do to prepare for AGI? We should just lay off people, right?
KLEIN: [laughs] I would not say it that way. I wouldn’t say just lay off people. I think that’s some of what we’re doing.
COWEN: No, not just, but step one.
KLEIN: Do you think that’s step one? Do you buy this DOGE’s preparation-for-AGI argument that you hear?
COWEN: I think maybe a fifth of them think that. Maybe it’s step two or step three, but it’s a pretty early step, right?
KLEIN: I think that the question of AI or AGI in the federal government, in anywhere — and this is one reason I’ve not bought this argument about DOGE — is you have to ask, “Well what is this AI or AGI doing? What is its value function? What prompt have you given it? What have you asked it to execute across the government and how?”
Alignment, which we have primarily talked about in terms of whether or not the AI, the superintelligence makes us all into paperclips, is a constant question of just near-term systems as well. I think the question of how should we prepare for AGI or for AI in the federal government first has to do with deciding what we would like the AI or the AGI to do. That could be different things to different areas.
My sense — talking to a bunch of people in the companies has helped me conceptualize this better — is that the first thing I would do is begin to ask, what do I think the opportunities of AI are, scientifically and in terms of different kinds of discoveries…
And this:
COWEN: Let me give you another right-wing view, and tell me what you think. The notion that the most important feature of state capacity is whether a state has enough of its citizens willing to fight and die for it. In that case, the United States, Israel, but a pretty small number of nations have high state capacity, and most of Western Europe really does not because they don’t have militaries that mean anything. Is that just the number one feature of abundance in state capacity?
Recommended, obviously.
What Did We Learn From Torturing Babies?
As late as the 1980s it was widely believed that babies do not feel pain. You might think that this was an absurd thing to believe given that babies cry and exhibit all the features of pain and pain avoidance. Yet, for much of the 19th and 20th centuries, the straightforward sensory evidence was dismissed as “pre-scientific” by the medical and scientific establishment. Babies were thought to be lower-evolved beings whose brains were not yet developed enough to feel pain, at least not in the way that older children and adults feel pain. Crying and pain avoidance were dismissed as simply reflexive. Indeed, babies were thought to be more like animals than reasoning beings and Descartes had told us that an animal’s cries were of no more import than the grinding of gears in a mechanical automata. There was very little evidence for this theory beyond some gesturing’s towards myelin sheathing. But anyone who doubted the theory was told that there was “no evidence” that babies feel pain (the conflation of no evidence with evidence of no effect).
Most disturbingly, the theory that babies don’t feel pain wasn’t just an error of science or philosophy—it shaped medical practice. It was routine for babies undergoing medical procedures to be medically paralyzed but not anesthetized. In one now infamous 1985 case an open heart operation was performed on a baby without any anesthesia (n.b. the link is hard reading). Parents were shocked when they discovered that this was standard practice. Publicity from the case and a key review paper in 1987 led the American Academy of Pediatrics to declare it unethical to operate on newborns without anesthesia.
In short, we tortured babies under the theory that they were not conscious of pain. What can we learn from this? One lesson is humility about consciousness. Consciousness and the capacity to suffer can exist in forms once assumed to be insensate. When assessing the consciousness of a newborn, an animal, or an intelligent machine, we should weigh observable and circumstantial evidence and not just abstract theory. If we must err, let us err on the side of compassion.
Claims that X cannot feel or think because Y should be met with skepticism—especially when X is screaming and telling you different. Theory may convince you that animals or AIs are not conscious but do you want to torture more babies? Be humble.
We should be especially humble when the beings in question are very different from ourselves. If we can be wrong about animals, if we can be wrong about other people, if we can be wrong about our own babies then we can be very wrong about AIs. The burden of proof should not fall on the suffering being to prove its pain; rather, the onus is on us to justify why we would ever withhold compassion.
Hat tip: Jim Ward for discussion.
The Shortage that Increased Ozempic Supply
It sometimes happens that a patient needs a non-commercially-available form of a drug, a different dosage or a specific ingredient added or removed depending on the patient’s needs. Compounding pharmacies are allowed to produce these drugs without FDA approval. Moreover, since the production is small-scale and bespoke the compounded drugs are basically immune from any patent infringement claims. The FDA, however, also has an oddly sensible rule that says when a drug is in shortage they will allow it be compounded, even when the compounded version is identical to the commercial version.
The shortage rule was meant to cover rare drugs but when demand for the GLP-1 drugs like Ozempic and Zepbound skyrocketed, the FDA declared a shortage and big compounders jumped into the market offering these drugs at greatly reduced prices. Moreover, the compounders advertised heavily and made it very easy to get a “prescription.” Thus, the GLP-1 compounders radically changed the usual story where the patient asks the compounder to produce a small amount of a bespoke drug. Instead the compounders were selling drugs to millions of patients.
Thus, as a result of the shortage rule, the shortage led to increased supply! The shortage has now ended, however, which means you can expect to see many fewer Hims and Hers ads.
Scott Alexander makes an interesting point in regard to this whole episode:
I think the past two years have been a fun experiment in semi-free-market medicine. I don’t mean the patent violations – it’s no surprise that you can sell drugs cheap if you violate the patent – I mean everything else. For the past three years, ~2 million people have taken complex peptides provided direct-to-consumer by a less-regulated supply chain, with barely a fig leaf of medical oversight, and it went great. There were no more side effects than any other medication. People who wanted to lose weight lost weight. And patients had a more convenient time than if they’d had to wait for the official supply chain to meet demand, get a real doctor, spend thousands of dollars on doctors’ visits, apply for insurance coverage, and go to a pharmacy every few weeks to pick up their next prescription. Now pharma companies have noticed and are working on patent-compliant versions of the same idea. Hopefully there will be more creative business models like this one in the future.
The GLP-1 drugs are complex peptides and the compounding pharmacies weren’t perfect. Nevertheless, I agree with Scott that, as with the off-label market, the experiment in relaxed FDA regulation was impressive and it does provide a window onto what a world with less FDA regulation would look like.
Hat tip: Jonathan Meer.
More British DOGE
Sir Keir Starmer is abolishing NHS England as Labour embarks on the biggest reorganisation of the health service for more than a decade.
The prime minister said that scrapping the arm’s-length body would bring “management of the NHS back into democratic control” and reduce spending on “two layers of bureaucracy”.
He said the quango, responsible for the day-to-day running of the health service, was the ultimate example of “politicians almost not trusting themselves, outsourcing everything to different bodies … to the point you can’t get things done”.
Starmer argued: “I don’t see why the decision about £200 billion of taxpayer money on something as fundamental to our security as the NHS should be taken by an arm’s-length body.”
NHS England will now be brought back under the control of the Department of Health and Social Care (DHSC), and the two organisations will be merged over the next two years, leading to about 10,000 job cuts.
Here is more from the Times of London.
Germany fact of the day
Germany opened its doors a decade ago to nearly 1 million Syrians, taking in more than any other country in Europe. Today, some 6,000 Syrian doctors make up the single largest group of foreign-born physicians, filling vital gaps in care at hospitals and clinics from the Alps to the Baltic Sea. That is especially true in rural areas, where attracting doctors can be hard. But even in big cities, Syrian doctors now make up the majority of attending physicians at some medical practices.
Here is more from The Washington Post. Here is my previous post on Syrians in Germany.
Visits to the Doctor, Per Year
The number of times people visit the doctor per year varies tremendously across OECD countries from a low of 2.9 in Chile to a high of 17.5 (!) in Korea. I haven’t run the numbers officially but it doesn’t seem that there is much correlation with medical spending per capita or life expectancy.
Data can be found here. 
Hat tip: Emil Kirkegaard on X.
My Conversation with Carl Zimmer
Here is the audio, video, and transcript. Here is part of the episode summary:
He joins Tyler to discuss why it took scientists so long to accept airborne disease transmission and more, including why 19th-century doctors thought hay fever was a neurosis, why it took so long for the WHO and CDC to acknowledge COVID-19 was airborne, whether ultraviolet lamps can save us from the next pandemic, how effective masking is, the best theory on the anthrax mailings, how the U.S. military stunted aerobiology, the chance of extraterrestrial life in our solar system, what Lee Cronin’s “assembly theory” could mean for defining life itself, the use of genetic information to inform decision-making, the strangeness of the Flynn effect, what Carl learned about politics from growing up as the son of a New Jersey congressman, and much more.
Here is an excerpt:
COWEN: Over time, how much will DNA information enter our daily lives? To give a strange example, imagine that, for a college application, you have to upload some of your DNA. Now to unimaginative people, that will sound impossible, but if you think about the equilibrium rolling itself out slowly — well, at first, students disclose their DNA, and over time, the DNA becomes used for job hiring, for marriage, in many other ways. Is this our future equilibrium, that genetic information will play this very large role, given how many qualities seem to be at least 40 percent to 60 percent inheritable, maybe more?
ZIMMER: The term that a scientist in this field would use would be heritable, not inheritable. Inheritability is a slippery thing to think about. I write a lot about that in my book, She Has Her Mother’s Laugh, which is about heredity in general. Heritability really is just saying, “Okay, in a certain situation, if I look at different people or different animals or different plants, how much of their variation can I connect with variation in their genome?” That’s it. Can you then use that variability to make predictions about what’s going to happen in the future? That is a totally different question in many —
COWEN: But it’s not totally different. Your whole family’s super smart. If I knew nothing about you, and I knew about the rest of your family, I’d be more inclined to let you into Yale, and that would’ve been a good decision. Again, only on average, but just basic statistics implies that.
ZIMMER: You’re very kind, but what do you mean by intelligent? I’d like to think I’m pretty good with words and that I can understand scientific concepts. I remember in college getting to a certain point with calculus and being like, “I’m done,” and then watching other people sail on.
COWEN: Look, you’re clearly very smart. The New York Times recognizes this. We all know statistics is valid. There aren’t any certainties. It sounds like you’re running away from the science. Just endorse the fact you came from a very smart family, and that means it’s quite a bit more likely that you’ll be very smart too. Eventually, the world will start using that information, would be the auxiliary hypothesis. I’m asking you, how much will it?
ZIMMER: The question that we started with was about actually uploading DNA. Then the question becomes, how much of that information about the future can you get out of DNA? I think that you just have to be incredibly cautious about jumping to conclusions about it because the genome is a wild and woolly place in there, and the genome exists in environments. Even if you see broad correlations on a population level, as a college admission person, I would certainly not feel confident just scanning someone’s DNA for information in that regard.
COWEN: Oh, that wouldn’t be all you would do, right? They do plenty of other things now. Over time, say for job hiring, we’ll have the AI evaluate your interview, the AI evaluate your DNA. It’ll be highly imperfect, but at some point, institutions will start doing it, if not in this country, somewhere else — China, Singapore, UAE, wherever. They’re not going to be so shy, right?
ZIMMER: I can certainly imagine people wanting to do that stuff regardless of the strength of the approach. Certainly, even in the early 1900s, we saw people more than willing to use ideas about inherited levels of intelligence to, for example, decide which people should be institutionalized, who should be allowed into the United States or not.
For example, Jews were considered largely to be developmentally disabled at one point, especially the Jews from Eastern Europe. We have seen that people are certainly more than eager to jump from the basic findings of DNA to all sorts of conclusions which often serve their own interests. I think we should be on guard that we not do that again.
And:
COWEN: If we take the entirety of science, you’ve written on many topics in a very useful way, science policy. Where do you think your views are furthest from the mainstream or the orthodoxy? Where do you have the weirdest take relative to other people you know and respect? I think we should just do plenty of human challenge trials. That would be an example of something you might say, but what would the answer be for you?
I very much enjoyed Carl’s latest book Air-Borne: The Hidden History of the Air We Breathe.
Hire Don’t Fire at the FDA
As a longtime critic of the FDA, you might expect me to support firing FDA employees—not so! My focus has always been on reducing approval time and costs to speed drugs to patients and increase the number of new drugs. Cutting staff is more likely to slow approvals and raise costs.
To be fair, we’re talking about the firing of some 200 probationary employees from a total of some 20,000. Unusual but not earth shaking. But the firings are indiscriminate, and as I explain below, the FDA is a peculiar target for cost-cutting because user fees under PDUFA cover a significant share of the FDA’s budget so its workers are among the cheapest federal employees. So what is the point? Shock and awe in advance of bigger reforms for the FDA? Perhaps. Regardless, I think we should keep in mind the big picture on staff and speed.
The Prescription Drug User Fee Act of 1992 (PDUFA) provides strong evidence that with more staff the FDA works faster to get new and better drugs to patients. Before PDUFA, drug approvals languished at the FDA simply due to a lack of staff—harming both drug companies and patients. Congress should have increased FDA funding, as the benefits would have far outweighed the costs, but Congress failed. Instead, PDUFA created a workaround: drug firms agreed to pay user fees, with the condition that the funds be used for drug reviewers and that the FDA be held to strict review standards.
PDUFA was a tremendous success. Carpenter et al., Olson, Berndt et al. and others all find that PDUFA shortened review times and it did so primarily through the mechanism of hiring more staff. Thus, Carpenter et al. report “NDA review times shortened by 3.3 months for every 100 additional FDA staff.” Moreover, the faster approval times came at little to no expense of reduced safety. Thus, Berndt et al. report:
implementation of the PDUFAs led to substantial incremental reductions in approval times beyond what would have been observed in the absence of these legislative acts. In addition, our preliminary examination of the trends in the number of new molecular entity withdrawals, frequently used as a proxy to assess the FDA’s safety record, suggests that the proportion of approvals ultimately leading to safety withdrawals prior to PDUFA and during PDUFA I and II were not statistically different.
And in a later analysis Philipson et al. find that:
more rapid access of drugs on the market enabled by PDUFA saved the equivalent of 140,000 to 310,000 life years. Additionally, we estimate an upper bound on the adverse effects of PDUFA based on drugs submitted during PDUFA I/II and subsequently withdrawn for safety reasons, and find that an extreme upper bound of about 56,000 life years were lost. This estimate is an extreme upper bound as it assumes all withdrawals since the inception of PDUFA were due to PDUFA and that there were no patients who benefitted from the withdrawn drugs.
If we’re going to have FDA review, it should be fast and efficient. We need to shift the focus from the FDA’s balance sheet in the Federal budget to the patients it serves—more staff means faster reviews, better access to treatments, and a healthier society.
More generally, government regulation, not staffing, is the real problem. Cut regulation, and staff cuts can follow. Cut staff without cutting regulation, and the morass only gets worse.
Does Peer Review Penalize Scientific Risk Taking?
Scientific projects that carry a high degree of risk may be more likely to lead to breakthroughs yet also face challenges in winning the support necessary to be carried out. We analyze the determinants of renewal for more than 100,000 R01 grants from the National Institutes of Health between 1980 and 2015. We use four distinct proxies to measure risk taking: extreme tail outcomes, disruptiveness, pivoting from an investigator’s prior work, and standing out from the crowd in one’s field. After carefully controlling for investigator, grant, and institution characteristics, we measure the association between risk taking and grant renewal. Across each of these measures, we find that risky grants are renewed at markedly lower rates than less risky ones. We also provide evidence that the magnitude of the risk penalty is magnified for more novel areas of research and novice investigators, consistent with the academic community’s perception that current scientific institutions do not motivate exploratory research adequately.
That is from a new NBER working paper by
Reforming the NIH
It seems the Trump proposal to simply cut overhead to fifteen percent will not stand up in the courts, at least not without Congressional approval? Nonetheless a few of you have asked me what I think of the idea.
My preferred reforms for the NIH include the following:
1. Cap pre-specified overhead at 25 percent, down from a range running up to 60 percent.
2. Encourage more coverage of overhead in the proposals themselves, where the researchers are accountable for how the overhead funds are spent. Severely limit how much the “overhead” cross-subsidizes other university functions, as is currently the case.
3. Fund a greater number of proposals, with the money coming from overhead reductions, as outlined in #1 and #2.
4. Set up a new, fully independent biomedical research arm of the federal government, based on DARPA-like principles. In fact this was seriously proposed a few years ago, with widespread (but insufficient) support.
I would note a few additional points, which have been covered in earlier MR posts over the years:
5. The NIH could not get its act together during Covid to make fast grants with sufficient rapidity during a time of crisis. They performed much worse than did say the NSF.
6. A while back the NIH set up a program to make riskier grants. The program did not in fact make riskier grants.
7. The NIH killed the idea of an independent DARPA-like biomedical research agency, fearing it would limit the size and influence of the NIH itself.
8. The submission forms, their length, and the associated processes are absurd. Whether or not the costs there are high in an absolute sense, it is a sign the current NIH is far too obsessed with process, as happens to just about every mature bureaucracy.
At this point it is obvious that the NIH cannot reform itself. It is also obvious that a slower, technocratic approach just gives the interest groups — in this case it is “the states” most of all — time to mobilize to protect the current NIH. There are universities in many Congressional districts and a fair amount of money at stake.
I do not per se favor a move to fifteen percent overhead, as I do understand the associated costs on scientific research. Nonetheless I take very seriously the possibility that a radical “thoughtless” cut now stands some chance of getting us to where we ought to be in the longer run, especially since subsequent administrations will get further cracks at this problem. They can up overhead to 25 percent, and set up the new DARPA-H. I just don’t see why that is impossible, and it may not even be unlikely. So what exactly is your discount rate and risk aversion here?
I feel the defenses of the NIH I am reading do not take the entire broader analysis seriously enough. They do not take sufficiently seriously that the writers themselves have failed to adequately reform the NIH. And over time, without serious reform, the bureaucratic stultification will only get worse.
The Licensing Racket
I review a very good new book on occupational licensing, The Licensing Racket by Rebecca Haw Allensworth in the WSJ.
Most people will concede that licensing for hair braiders and interior decorators is excessive while licensing for doctors, nurses and lawyers is essential. Hair braiders pose little to no threat to public safety, but subpar doctors, nurses and lawyers can ruin lives. To Ms. Allensworth’s credit, she asks for evidence. Does occupational licensing protect consumers? The author focuses on the professional board, the forgotten institution of occupational licensing.
Governments enact occupational-licensing laws but rarely handle regulation directly—there’s no Bureau of Hair Braiding. Instead, interpretation and enforcement are delegated to licensing boards, typically dominated by members of the profession. Occupational licensing is self-regulation. The outcome is predictable: Driven by self-interest, professional identity and culture, these boards consistently favor their own members over consumers.
Ms. Allensworth conducted exhaustive research for “The Licensing Racket,” spending hundreds of hours attending board meetings—often as the only nonboard member present. At the Tennessee board of alarm-system contractors, most of the complaints come from consumers who report the sort of issues that licensing is meant to prevent: poor installation, code violations, high-pressure sales tactics and exploitation of the elderly. But the board dismisses most of these complaints against its own members, and is far more aggressive in disciplining unlicensed handymen who occasionally install alarm systems. As Ms. Allensworth notes, “the board was ten times more likely to take action in a case alleging unlicensed practice than one complaining about service quality or safety.”
She finds similar patterns among boards that regulate auctioneers, cosmetologists and barbers. Enforcement efforts tend to protect turf more than consumers. Consumers care about bad service, not about who is licensed, so take a guess who complains about unlicensed practitioners? Licensed practitioners. According to Ms. Allensworth, it was these competitor-initiated cases, “not consumer complaints alleging fraud, predatory sales tactics, and graft,” where boards gave the stiffest penalties.
You might hope that boards that oversee nurses and doctors would prioritize patient safety, but Ms. Allensworth’s findings show otherwise. She documents a disturbing pattern of boards that have ignored or forgiven egregious misconduct, including nurses and physicians extorting sex for prescriptions, running pill mills, assaulting patients under anesthesia and operating while intoxicated.
Read the whole thing.
What should I ask Sheilagh Ogilvie?
She is a Canadian economic historian at Oxford, here is from her home page:
I am an economic historian. I explore the lives of ordinary people in the past and try to explain how poor economies get richer and improve human well-being. I’m interested in how social institutions – the formal and informal constraints on economic activity – shaped economic development between the Middle Ages and the present day.
And:
My current research focusses on serfdom, human capital, state capacity, and epidemic disease. Past projects analysed guilds, merchants, communities, the family, gender, consumption, finance, proto-industry, historical demography, childhood, and social capital. I have a particular interest in the economic and social history of Central and Eastern Europe.
Here is her Wikipedia page. Her book on guilds is well known, and her latest is Controlling Contagion: Epidemics and Institutions from the Black Death to Covid. Here are her main research papers.
So what should I ask her?
Genetic Prediction and Adverse Selection
In 1994 I published Genetic Testing: An Economic and Contractarian Analysis which discussed how genetic testing could undermine insurance markets. I also proposed a solution, genetic insurance, which would in essence insure people for changes in their health and life insurance premiums due to the revelation of genetic data. Later John Cochrane would independently create Time Consistent Health Insurance a generalized form of the same idea that would allow people to have long term health insurance without being tied to a single firm.
The Human Genome Project completed in 2003 but, somewhat surprisingly, insurance markets didn’t break down, even though genetic information became more common. We know from twin studies that genetic heritability is very large but it turned out that the effect from each gene variant is very small. Thus, only a few diseases can be predicted well using single-gene mutations. Since each SNP has only a small effect on disease, to predict how genes influence disease we would need data on hundreds of thousands, even millions of people, and millions of their SNPs across the genome and their diseases. Until recently, that has been cost-prohibitive and as a result the available genetic information lacked much predictive power.
In an impressive new paper, however, Azevedo, Beauchamp and Linnér (ABL) show that data from Genome-Wide Association Studies can be used to create polygenic risk indexes (PGIs) which can predict individual disease risk from the aggregate effects of many genetic variants. The data is prodigious:
We analyze data from the UK Biobank (UKB) (Bycroft et al., 2018; Sudlow et al., 2015). The UKB contains genotypic and rich health-related data for over 500,000 individuals from across the United Kingdom who were between 40 and 69 years old at recruitment (between 2006 and 2010). UKB data is linked to the UK’s National Health Service (NHS), which maintains detailed records of health events across the lifespan and with which 98% of the UK population is registered (Sudlow et al., 2015). In addition, all UKB participants took part in a baseline assessment, in which they provided rich environmental, family history, health, lifestyle, physical, and sociodemographic data, as well as blood, saliva, and urine samples.
The UKB contains genome-wide array data for ∼800,000 genetic variants for ∼488,000 participants.
So for each of these individuals ABL construct risk indexes and they ask how significant is this new information for buying insurance in the Critical Illness Insurance market:
Critical illness insurance (CII) pays out a lump sum in the event that the insured person gets diagnosed with any of the medical conditions listed on the policy (Brackenridge et al., 2006). The lump sum can be used as the policyholder wishes. The policy pays out once and is thereafter terminated.
… Major CII markets include Canada, the United Kingdom, Japan, Australia, India, China, and Germany. It is estimated that 20% of British workers were covered by a CII policy in 2009 (Gatzert and Maegebier, 2015). The global CII market has been valued at over $100 billion in 2021 and was projected to grow to over $350 billion by 2031 (Allied Market Research, 2022).
The answer, as you might have guessed by now, is very significant. Even though current PGIs explain only a fraction of total genetic risk, they are already predictive enough so that it would make sense for individuals with high measured risk to purchase insurance, while those with low-risk would opt out—leading to adverse selection that threatens the financial sustainability of the insurance market.
Today, the 500,000 people in the UK’s Biobank don’t know their PGIs but in principle they could and in the future they will. Indeed, as GWAS sample sizes increase, PGI betas will become more accurate and they will be applied to a greater fraction of an individual’s genome so individual PGIs will become increasingly predictive, exacerbating selection problems in insurance markets.
If my paper was a distant early warning, Azevedo, Beauchamp, and Linnér provide an early—and urgent—warning. Without reform, insurance markets risk unraveling. The authors explore potential solutions, including genetic insurance, community rating, subsidies, and risk adjustment. However, the effectiveness of these measures remains uncertain, and knee-jerk policies, such as banning insurers from using genetic information, could lead to the collapse of insurance altogether.
FDA Deregulation of E-Cigarettes Saved Lives and Spurred Innovation
What would happen to drug development if the FDA lost its authority to prohibit new drugs? Would research and development boom and lives be saved? Or would R&D decline and lives be lost to a flood of unsafe and ineffective drugs? Or perhaps R&D would decline as demand for new drugs faltered due to public hesitation in the absence of FDA approval? In an excellent new paper Pesko and Saenz examine one natural experiment: e-cigarettes.
The FDA banned e-cigarettes as unapproved drugs soon after their introduction in the United States. The FDA had previously banned other nicotine infused products. Thus, it was surprising when in 2010 the FDA was prohibited from regulating e-cigarettes as a drug/device when a court ruled that Congress had intended for e-cigarettes to be regulated as a tobacco product not as a drug.
As of 2010, therefore, e-cigarettes were not FDA regulated:
…e–cigarette companies were able to bypass the lengthy and costly drug approval process entirely. Additionally, without FDA drug regulation, e–cigarette companies could also freely enter the market, modify products without approval, and bypass extensive post–market reporting requirements and quality control standards.
Indeed, it wasn’t until 2016 that the FDA formally “deemed” e-cigarettes as tobacco products (deemed since they don’t actually contain tobacco) and approvals under the less stringent tobacco regulations were not required until 2020. For nearly a decade, therefore, e-cigarettes were almost entirely unregulated and then lightly regulated under the tobacco framework. So, what happened during this period?
Pesko and Saenz show that FDA deregulation led to a boom in e-cigarette research and development which improved e-cigarettes and led to many lives saved as people switched from smoking to vaping.
The boom in research and development is evidenced by a very large increase in US e-cigarette patents. We do not see a similar increase in Australia (where e-cigarettes were not deregulated) nor do we see an increase in non e-cigarette smoking cessation products (figure 1a of their paper not shown here).

Estimating the decline in smoking and smoking-attributable mortality (SAM) is more difficult but the authors assemble a large collection of data broken down by demographics and they estimate that prohibiting the FDA from regulating e-cigarettes reduced smoking attributable mortality by nearly 10% on average each year from 2011-2019 for a total savings of some 677,000 life-years.
The authors pointedly compare what happened under deregulation of e-cigarettes–innovation and lives saved–with what happened to similar smoking cessation products that remained under FDA regulation–stagnation and no reduction in smoking attributable mortality.
A key takeaway on the slowness of FDA drug regulation is that it took 9 years before nicotine gum could be sold with a higher nicotine strength, 12 years before it could be sold OTC, and 15 years before it could be sold with a flavor. Further, a recent editorial laments that there has been largely non–existent innovation in FDA–approved smoking cessation drugs since 2006 (Benowitz et al., 2023). In particular, the “world’s oldest smoking cessation aid” cyctisine, first brought to market in 1964 in Bulgaria (Prochaska et al., 2013), and with quit success rates exceeding single forms of nicotine replacement therapy (NRT) (Lindson et al., 2023), is not approved as a drug in the United States.
The authors conclude, “this situation raises concern that drugs may be over–regulated in the United States…”. Quite so.
Addendum: A quick review on the FDA literature. In addition to classic works by Peltzman on the 1962 Amendments and by myself on what we can learn about the FDA from off-label pricing we have a spate of recent new papers including Parker Rogers, which I covered earlier:
In an important and impressive new paper, Parker Rogers looks at what happens when the FDA deregulates or “down-classifies” a medical device type from a more stringent to a less stringent category. He finds that deregulated device types show increases in entry, innovation, as measured by patents and patent quality, and decreases in prices. Safety is either negligibly affected or, in the case of products that come under potential litigation, increased.
and Isakov, Lo and Montazerhodjat which finds that FDA statistical standards tend to be too conservative, especially for drugs meant to treat deadly diseases (see my comments on their paper and more links in Is the FDA Too Conservative or Too Aggressive?)
See also FDA commentary, for much more from sunscreens to lab developed tests.