Category: Medicine
Capitalism and Modernity
Jesús Fernández-Villaverde, one of the few economists in the world equally at home solving stochastic dynamic optimization problems as with sociological theory and history, has an excellent series of twitter posts on capitalism and modernity.
JFV: I have been reading (and re-reading) a lot of social theory.
What strikes me is that most critics of “capitalism” (whatever “capitalism” might mean, and regardless of the value of those critiques) are really critics of modernity, understood as the organization of society around technology, formal institutions, and rational criteria.
I teach the economic history of the Soviet Union and socialist China, and all the pathologies (pollution, reliance on fossil fuels, inequality, depersonalization, consumerism, alienation, you name it) that you can find in a poor neighborhood of 2026 Philadelphia appeared in the same way, or even more, in a factory in Leningrad in 1970 or on a collective farm in Jiangsu in 1978.
Critics seem to lack a vocabulary (or, if you prefer, a cognitive framework) for distinguishing “capitalism” from modernity. For example, people everywhere tend to link personal relationships to displays of consumption. There are likely deep evolutionary reasons for this. De Beers did not invent spending a lot of money on a useless engagement ring: it rode a pre-existing disposition into a particular form of consumption. Couples in Leipzig in 1982 were as interested in conspicuous consumption as those in Chicago in 2026. Talking about “Love and the Cultural Contradictions of Capitalism” misses the point completely.
Of course, you can try, as some of the more perceptive Trotskyists did, to argue that the Soviet Union or China were not truly socialist countries, but this is just a lazy application of the “no true Scotsman” fallacy, and, consequently, their complaints failed to gain much traction outside some departments of cultural studies.
But this is not just a matter of poor analytic skills, as bad as those are. More importantly, it means that 99% of the policy proposals activists put on the table to correct the problems of “capitalism” are doomed to fail because they do not understand where the root cause of the phenomena they complain about lies.
I see this at the university. Do you think the corporation you deal with is self-serving and incompetent? Wait until you need to deal with the Graduate School at a private Ivy League university. The incentive problems (asymmetric information, career concerns, lack of timely feedback, pressure toward conformity) that cause dysfunction in the former are even more pronounced in the latter because of the absence of a profit motive, the sharpest disciplinary mechanism.
At a very fundamental level, Marx got modernity wrong; Weber got it right. Time to spend much less time with Marx and much, much more time with Weber.
Here’s the second post:
Many readers yesterday asked for more concrete examples of what I have in mind regarding the distinctions between features inherent to modernity and those inherent to “capitalism.”
Imagine we have a functioning socialist commonwealth. For simplicity, I will call it the SC.
Imagine also that this SC aims to provide state-of-the-art medical care to its citizens. This is not about superfluous consumption. It is about the desire to provide good preventive care, adequate treatment, palliative care, and so on.
Soon, you realize that you need the scientific-technological complex that develops advanced mRNA vaccines and, even more importantly, the industrial capacity to produce tens of millions of doses at short notice when a new virus arrives or an old one mutates. These are sophisticated processes that involve coordinating millions of individuals with diverse knowledge, skills, and personalities.
But it does not stop there. You will need to produce thousands of MRIs, scanners, FLASH radiotherapy machines, and all the bewildering array of equipment you find in a top hospital.
And I insist: wanting to be treated with the latest oncological equipment if you get cancer is not frivolity. It is a deep human desire that a good society (any society, really) should attempt to provide.
How are you going to accomplish all this? An SC does not want to use private property, so it relies on some form of public property. But public ownership is not the main issue. The real issue is that the SC would need to organize large bureaucratic organizations. Without them, it cannot develop and deploy vaccines, MRIs, scanners, and the rest. The need to scale is the key mechanism at play, not who owns the property.
And, because of their scale, these large bureaucratic organizations will suffer the type of problems that critics of “capitalism” attribute to “capitalism.” The organization will be impersonal and alienating, and inefficient due to career concerns, asymmetric information, conformity effects, and internal politics.
Moreover, because resource constraints hold in every human endeavor, some claims for medical treatment will be denied. The SC will not have enough resources to satisfy every medical demand (and medical demands are, for all practical purposes, unlimited), every demand for education, every demand for the environment, and every demand for this or that worthwhile cause. Sorry, yes, scarcity will always be with us, with or without AI.
Patients whose requests for medical treatment are denied will be particularly annoyed because the SC is built on the idea that such events cannot happen. At least in a “capitalist” society there is someone to blame (the “capitalist”).
Those who deny the need for large bureaucratic organizations are living in a fantasy world. I am pretty sure the day they are told they have prostate cancer, they will run to their closest large bureaucratic organization for treatment.
Those who deny the problems of large bureaucratic organizations, and how deeply irresoluble those problems are, have not seen how not-for-profits work. I have never seen more acrimonious fights than within not-for-profit organizations, where some shared sense of the common good unites members. The fights are fierce precisely because profits play no role.
I have been reading about these issues for nearly 40 years, and I have seen plenty of proposals to address the problems of large bureaucratic organizations. A favorite among many is “participation” or “more democracy” within the organization. No, sorry, more “participation” or “more democracy” only makes things worse. Yugoslavia taught us that you cannot run a large bureaucratic organization based on democratic participation (well, you only need to know some basic economics; Arrow’s impossibility theorem, anyone?).
Large bureaucratic organizations are essential to modern life, and they are full of problems, with or without “capitalism.”
This is what Weber understood and what Marx, who had an incredibly naïve view of the future, never grasped. Weber saw that bureaucracy is not a feature of “capitalism” but the institutional form modern society uses to coordinate large-scale tasks under rational, impersonal rules. Hospitals, ministries, armies, universities, and, yes, corporations all converge on the same form because it works at scale. The iron cage is not capitalist. It is modernity.
The third excellent post on whether capitalism created modernity which criticizes Quine and the analytic-synthetic distinction (!) is here.
On health care price transparency (from the comments)
From MR commentator Sure:
Generally such figures do not reside within the physicians’ office. On our side of the table we do some procedure with multiple specifications and generate some CPT code(s) (e.g. a lap cholycystectomy is 47562, add on a common bile duct exploration and it becomes a 47564, and if you just do cholangiography it becomes a 47563). Generally, we couple that with an ICD-10 code that specifies your exact disease (K80 for simple stones, K81 for cholecystitis, etc.). We then dump those codes into a computer.
Can either of those change? Absolutely, we find a bunch of friable neovasculature around the gallbladder, congrats you likely have cancer which means this surgery is now both a different CPT code and a different ICD-10 set. Maybe only one does – we find the gallbladder lacks an obstructing stone, but does have transmural inflammation then you get a new ICD-10 code. If we find that you actually have multiple obstructing stones and we need to go deeper into the biliary tree, then those are different CPTs.
Regardless, we do what is medically indicated, document the codes used.
At this point, unless your physician keeps billing fully in house, those get handled by a processer. Often, bills from multiple providers get handled by one processor who in turn gives insurance companies bills to their specifications. Often this involves a bunch things – where was the surgery done (through very complicated rules, critical access hospitals, for example, can charge more for the same surgery because the government wants to keep them solvent lest a bunch of people lose their local emergency room and OR), who was doing it (e.g. there is a different rate if you have medical trainees involved), and of course stuff about you (e.g. complex patients get reimbursed at higher rates with the expectation that, on average, the higher rates cover higher complication rates and insurance doesn’t incentvize surgeons to make all their complex patients drive for hours and hours). Then we get to the big buys – buyers. For Medicare, there are some committees that appear to be overwhelmingly ignorant of actual medical practice but they set baseline reimbursements for these CPT/ICD-10 combos. Those then get adjusted to account for regional costs, equity concerns, and only God knows what all else. These are normally set near the break even point on national average. Medicaid, typically, uses those rates as a baseline and then cuts them (hence why many physicians won’t take new Medicaid patients, the reimbursement rates often leave folks at a net loss). Private insurers add another layer of negotiation where they use their monopsony power to extract lower rates while, allegedly, assuring physicians of volume. The range of these negotiations can be exceedingly wide – insurers can have modifiers for quality of care (e.g. how many folks come back in the perioperative period), timeliness of care, and so on and so forth.
Okay, so somebody has haggled set a rate and we just assume that get the bog standard lap chole we have a price?
Of course not.
See that is just what has agreed, in theory, these medical services will be reimbursed at. Actual reimbursement involves a non-negligable risk on non-payment (e.g. insurance denies and the patient cannot or will not pay), delayed payment (and having to utilize credit lines to cover payroll when a large insurer has an IT glitch and doesn’t pay for two weeks is quite expensive), and of course variable legal and compliance costs. You might also be hit with clawbacks, partial payments, and a host of other payment uncertainty.
Okay, but’s lest assume a single CPT/ICD-10 setup, a prenegotiated rate that is paid on time without further processing costs, and everything is chill there. We got a price yet?
Of course not.
See all of the above is for just the surgeon’s professional fees – i.e. what is being paid for use of his hands. The OR itself? That’s a completely different bucket of money that has its own set of billing and negotiations. Facility fees make the professional fees look straight forward and simple.
But we are done now? Right?
Of course not.
See those were the professional fees for your surgeon. You also need an anesthesiologist (and/or his minions). And guess what, yep completely different bucket of money and price negotiation.
But we are done now?
Well, no. There may be different negotiations for lab fees (e.g. where does the CBC get billed), for tissue pathology, for any post-operative hospital services, and of course medications (which are billed completely differently if outpatient or inpatient) to name a few of the more common options.
There isn’t “a” price for a surgery. There are, potentially, a dozen diferent prices that can be combined in a multitude of ways with some buckets covered by one payer and other parts covered by another (and things get crazy fun when you have overlapping payers).
But aren’t there cash only surgical places with listed prices? Yes. And they have an extremely limited set of procedures with everything owned in house – i.e. a setup that is pretty much illegal to set up de novo post Obamacare.
Why does everyone have all these bizarre negotations. Why don’t you just pay the surgeon everything and then he pays the hospital, the anesthesiologist, the pathologist, etc. from that cut? Because that is an invitation for your surgeon to be charged with a crime. It is federal crime to underbill or to underbill when it comes to government monies (and in many states, private insurance monies). We are required not just to I Pencil up a price, but to make that price transparent to regulators. If a hospital wants to grant me cheaper OR time because I have reliable stream of patients, keep the OR cleaner (reducing turnaround time enough to fit another case per day in), and don’t create ancillary malpractice risk at the going rate … the hospital risks being tagged with inducement. If I negotiate a cheaper rate with the lab for my patients’ tests, it is considered prima facie evidence for kickbacks and I then have a positive burden to prove that I am not getting clandestine remuneration from the lab.
Separate, disjointed, billing through bureaucratic negotiation is legible. It is legible to the courts, to regulators, and to malpractice insurers.
But doesn’t all this massive change efficiency of care delivery?
Not that I can easily see. I have personal experience with IHS, TriCare, Kaiser, the VA, and for-profit, non-profit, and even prison care; full Beveridge like IHS is often the least efficient.So where do cash prices come from? Outside of cash only practices, those are overwhelmingly fictions that somebody pulled out of their nether regions in a likely futile attempt to BS the counterparty to an insurance negotiation.
Why is this all so complicated:
1. Principle agent. The patient has a wildly different incentive structure than the collective payer (insurance or government) and American healthcare is insanely deferential to the patient compared to alternatives. The folks with the most direct control feel at most a small fraction of the price pain have near zero incentive to economize for anything big.
2. Taxes. The original sin of American healthcare was making insurance, rather than medical procedures themselves, tax deductible. This creates very strong incentives for people to bundle non-healthcare into insurance premiums in hard to define manners (e.g. is a health insurer offering a rebate for gym membership incentivizing exercise, allowing folks who would already have gym memberships to pay pre-tax, or just selecting for healthier patients).
3. People are terrified of physician abuse. Most folks, even other physicians, have a very hard time knowing if their physician is taking them for a ride. So they turn to something powerful to regulate physicians. But, not knowing what actually matters, these folks find it extremely hard to navigate market transactions. Healthcare would far rather have 100 unattributable deaths and 2x costs than to have 1 attributable death that regulation could avoid.
4. A complete disconnect between what folks experience for prices (e.g. my tape easily costs 10x more than department store specials, my EMR internal word processor is an order of magnitude more expensive than MSWord let alone Emacs or the like) and how medical expenses run.
5. A failure to appreciate the costs of having things on standby. We have folks ready incase a simple IR procedure perfs the vessel walls. We have countless folks handy in case your infusion leads to anaphylaxis. Or your blood transfusion moves on to TRALI. Just opening the doors typically means that we need to have a few dozen physicians and their support staff available at all times. I’ve seen a simple gallbladder turn into a massive transfusion with staging, SICU, and the whole works. I have seen STD treatment turn into a catastrophic emergency of the sort that gets Derm to come in at oh ass hundred.None of those go away if we post prices. And a lot of people will be upset – somebody will decry us pricing differently for different patients – everyone deserves the same care at the same cost. Somebody will decry us for not pricing differently enough – people should be reward for making good decisions.
Long run, healthcare is going to get more expensive. I expect it will eventually be on part with mortgage payments (you know you live in your body 24/7). But there is an evergreen fantasy that … if only … then we could reduce prices.
You can’t. You can, maybe, make them rise more slowly, normally for harsh tradeoffs Americans won’t stand. And just about every significant intervention that really moves the price needle … is either selection (e.g. health share ministries have wildly healthier populations because they are heavily selected about drugs, promiscuity, and the rest) or given entirely back by the patient dying later. And the handful of things to do pass muster (e.g. HPV vaccination, Hep C treatment) … it becomes yet another morass of how much to pay whom.
Healthcare is not a normal market. We should stop pretending it could be one.
Revising Modern Principles
Here’s a revision I made to Modern Principles, my textbook with Tyler. Some things change dramatically, some things never change.

The economic value of eliminating cancer
This paper estimates the economic value to the United States of eliminating cancer mortality over a 35-year horizon beginning in 2030, which would eliminate 30.7 million cancer deaths with a total mortality burden of 380 million life-years. We quantify the economic value of this substantial reduction in cancer mortality by incorporating the monetized value of increased longevity. To value the longevity gains in monetary terms, we utilize the valuations used by the U.S. federal government in its cost-benefit evaluations of regulations. Eliminating cancer mortality generates $197 trillion in economic benefits over 35 years, corresponding to approximately $16,282 per American per year, or $41,684 per American household per year. If cancer elimination is viewed as an R&D investment, it yields an enormous internal rate of return, ranging from 570% to 1,024%, based on benchmarked R&D costs. In addition, we perform a sensitivity analysis by varying the elimination durations and the degree of success, using the benchmark case scenario in which cancer mortality is reduced by 80 percent over a 20-year transition. This achieves about 70 percent of the total economic value of full elimination above, corresponding to aggregate benefits of about $134 trillion, or approximately $11,112 per person per year.
That is from a new NBER working paper by
Physician Incomes and the Extreme Shortage of High IQ Workers
Physician incomes are extraordinarily high in the United States. A new NBER paper finds that U.S. physicians earn roughly two to four times as much as their counterparts in Canada, the Netherlands, and Sweden.
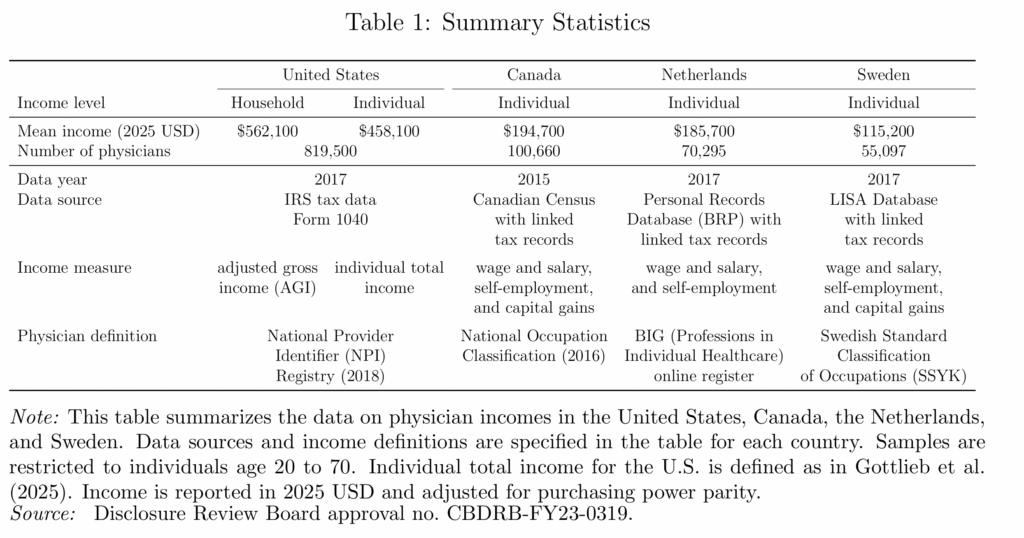
Why? Is it some feature particular to the US health care sector? Probably not. The same paper finds that physicians in the US have about the same relative income ranking as in Canada, the Netherlands, and Sweden. In other words, lots of high-skill workers in the US earn high incomes and physicians don’t look unusual relative to these other high-skill groups.
That is exactly what one would expect in an economy with an extreme shortage of high-IQ, high-skill workers. The US is a uniquely productive economy for high-skill workers which is why the US demand for foreign workers and the foreign demand to immigrate are so strong, especially at the high end.. By one estimate, “immigrants account for 32 percent of aggregate U.S. innovation.”
Immigration of high-skill workers such as with the H-1B and EB-1,2,3 programs, together with stronger U.S. education, is one way to reduce the shortage of high-skill workers. The alternative is simpler: make the economy less dynamic and less rewarding for talent. Then wages would fall and fewer ambitious people would bother coming. A solution but only if your preferred cure for scarcity is decline.
The rise of China as a global innovator in pharma (incentives matter)
This paper examines China’s transition from pharmaceutical “free rider” to global innovator over the last decade. In 2010, China accounted for less than 8% of global clinical trials; by 2020, it had surpassed the US in annual registered clinical trial volume. To study this transformation, we compile a comprehensive, synchronized database spanning the pharmaceutical drug development supply chain, covering scientific publications, clinical trials, drug development milestones for China, the U.S., and Europe, alongside drug sales and government policies over the same period. We provide strong evidence that China’s rise was primarily driven by the National Reimbursement Drug List (NRDL) reform, which dramatically expanded the effective market size for innovative drugs. We document a sharp rise in both the quantity (86% increase) and novelty of drug trials post reform, with growth concentrated in reform-exposed disease categories, first- or best-in-class drugs, and among domestic firms. A decomposition exercise reveals that the NRDL reform accounts for 43% of the growth in oncology trial activity, nearly doubling the combined contribution of upstream knowledge accumulation and talent flows (24%), while other government policies play a minor role. Finally, dynamic gains from induced innovation exceed the reform’s static gains in consumer access to innovative drugs by threefold, underscoring the importance of accounting for the reform’s long-run effects on innovation incentives in addition to near-term improvements in drug affordability.
That is from a new NBER working paper by
International Comparison of Physician Incomes
We compare physician incomes using tax data from the United States, Canada, Sweden, and the Netherlands. Physicians are concentrated in the top percentiles of the income distribution in all four countries, especially in the United States and certain specialties. Physician incomes are highest in the United States, and a decomposition shows that this mainly reflects differences in overall income distributions, rather than physicians’ locations in those distributions. This suggests that broader labor market differences, and thus physicians’ outside options, drive absolute incomes. Shifting US physicians’ incomes to match relative positions in other countries’ distributions would only marginally reduce healthcare spending.
By Aidan Buehler, et.al., from a new NBER working paper.
Tracing the Genetic Footprints of the UK National Health Service
The establishment of the UK National Health Service (NHS) in July 1948 was one of the most consequential health policy interventions of the twentieth century, providing universal and free access to medical care and substantially expanding maternal and infant health services. In this paper, we estimate the causal effect of the NHS introduction on early-life mortality and we test whether survival is selective. We adopt a regression discontinuity design under local randomization, comparing individuals born just before and just after July 1948. Leveraging newly digitized weekly death records, we document a significant decline in stillbirths and infant mortality following the introduction of the NHS, the latter driven primarily by reductions in deaths from congenital conditions and diarrhea. We then use polygenic indexes (PGIs), fixed at conception, to track changes in population composition, showing that cohorts born at or after the NHS introduction exhibit higher PGIs associated with contextually-adverse traits (e.g., depression, COPD, and preterm birth) and lower PGIs associated with contextually-valued traits (e.g., educational attainment, self-rated health, and pregnancy length), with effect sizes as large as 7.5% of a standard deviation. These results based on the UK Biobank data are robust to family-based designs and replicate in the English Longitudinal Study of Ageing and the UK Household Longitudinal Study. Effects are strongest in socioeconomically disadvantaged areas and among males. This novel evidence on the existence and magnitude of selective survival highlights how large-scale public policies can leave a persistent imprint on population composition and generate long-term survival biases.
Here is the link, via S.
If you have the right to die, you should have the right to try!
Ruxandra Teslo asks a good question:
I have a curiosity: why is it the case that it is easier to get MAID in Canada than it is to access experimental treatments which carry a higher risk? In the past, I used to think ppl do not like “deaths caused by the medical system”, but for MAID the prob of death is 100%…
The Canadians may be somewhat inconsistent on this point. Unfortunately, the Supreme Court has been consistent and has rejected medical self-defense arguments for physician assisted suicide and let stand an appeals court ruling that patients do not have a right to access drugs which have not yet been permitted for sale by the FDA (fyi, I was part of an Amici Curiae brief for this case).
Hat tip for the post title to Jason Crawford.
AI Won’t Automatically Accelerate Clinical Trials
Although I’m optimistic that AI will design better drug candidates, this alone cannot ensure “therapeutic abundance,” for a few reasons. First, because the history of drug development shows that even when strong preclinical models exist for a condition, like osteoporosis, the high costs needed to move a drug through trials deters investment — especially for chronic diseases requiring large cohorts. And second, because there is a feedback problem between drug development and clinical trials. In order for AI to generate high-quality drug candidates, it must first be trained on rich, human data; especially from early, small-n studies.
…Recruiting 1000 patients across 10 sites takes time; understanding and satisfying unclear regulatory requirements is onerous and often frustrating; and shipping temperature-sensitive vials to research hospitals across multiple states takes both time and money.
…For many diseases, however, the relevant endpoints take a very long time to observe. This is especially true for chronic conditions, which develop and progress over years or decades. The outcomes that matter most — such as disability, organ failure, or death — take a long time to measure in clinical trials. Aging represents the most extreme case. Demonstrating an effect on mortality or durable healthspan would require following large numbers of patients for decades. The resulting trial sizes and durations are enormous, making studies extraordinarily expensive. This scale has been a major deterrent to investment in therapies that target aging directly.
The Cassidy Report on the FDA
Senator Bill Cassidy (R-La.) released a new report on how to modernize the FDA. It has some good material.
… FDA’s process for reviewing new products can be an unpredictable “black box.” FDA teams can differ greatly in the extent to which they require testing or impose standards that are not calibrated to the relevant risks. The perceived disconnect between the forward leaning rhetoric and thought leadership of senior FDA officials and cautious reviewer practice creates further unpredictability. This uncertainty dampens investment and increases the time it takes for patients to receive new therapies.
Companies report that they face a “reviewer lottery,” where critical questions hinge on the approach of a small number of individuals at FDA. Some FDA review teams are creative and forward-leaning, helping developers design programs and overcome obstacles to get needed products to patients, without cutting corners. FDA’s Oncology Center of Excellence (OCE), for example, is repeatedly identified as a model for providing predictable yet flexible options for bringing new drugs to cancer patients. OCE is now a dialogue-based regulatory paradigm that has facilitated efforts by academia, industry, the National Institutes of Health (NIH), and others to develop new cancer therapies and launch innovative programs and pilots like Project Orbis, RealTime Oncology Review.
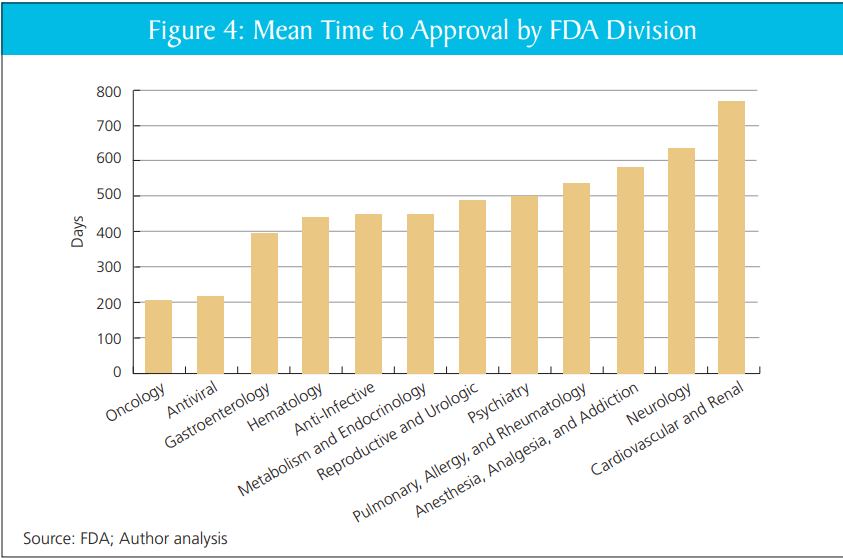
That’s quite right. In my report with DiMasi and Milne, we show that review times vary markedly within the FDA, across divisions, without clear cause. Put aside the big questions of FDA or no FDA–scaling the practices of the better-performing divisions would likely yield large gains.
Mike Doherty further asks the AI what Alex Tabarrok would think of the Cassidy report. It replies:
Strongest features: It correctly diagnoses FDA as a bottleneck to innovation, emphasizes “least burdensome” evidence, calls for streamlined pathways (505(b)(2)-style for biologics, biosimilar simplification), and worries about U.S. losing early-phase trials to other countries. This is very much in Tabarrok’s wheelhouse: regulation as a hidden tax on innovation and growth.
Weakest features: It rarely quantifies tradeoffs, almost never confronts the “invisible graveyard” of patients who never see therapies because of delay, and treats reforms as marginal tweaks rather than testing fundamentally different regulatory models (e.g., insurance-based approval, private certification, or sunset/experimentation with parallel regimes).
If you imagine this as a draft memo handed to Tabarrok, he’d likely say: “Good directionally; now add 50% more economics, 50% more quantification, and 100% more willingness to experiment with institutional competition.”
Yeah, pretty good.
Addendum: In other FDA news see also Adam Kroetsch on Will Bayesian Statistics Transform Trials?
Addendum 2: FDA has now agreed to review Moderna’s flu vaccine which is good although the course reversal obviously speaks to the unpredictability of the FDA.
The cocaine problem seems to be getting worse again
Colombian coca cultivation fell dramatically between 2000 and 2015, a period that saw intense U.S.-backed eradication and interdiction efforts. That progress reversed in 2015, when peace talks and legal rulings in Colombia opened enforcement gaps. Coca plantation has since increased to record levels, which coincided with a sharp rise in cocaine-related overdose deaths in the U.S. We estimate how much of that rise can be causally attributed to Colombia’s new coca boom. Leveraging the unforeseen coca supply shock and cross-county differences in pre-shock cocaine exposure, we find that the surge in supply caused an immediate rise in overdose mortality in the U.S. Our analysis estimates on the order of 1,000–1,500 additional U.S. deaths per year in the late 2010s can be attributed to Colombia’s cocaine boom. Implicit annual loss in American statistical life values about $48,000 per hectare of cultivation in Colombia. If left untamed, the current level of coca cultivation (over 230,000 ha in 2022) may impose on the order of $10 billion per year in costs via overdose fatalities.
That is from a new NBER working paper by Xinming Du, Benjamin Hansen, Shan Zhang, and Eric Zou.
I Regret to Inform You that the FDA is FDAing Again
I had high hopes and low expectations that the FDA under the new administration would be less paternalistic and more open to medical freedom. Instead, what we are getting is paternalism with different preferences. In particular, the FDA now appears to have a bizarre anti-vaccine fixation, particularly of the mRNA variety (disappointing but not surprising given the leadership of RFK Jr.).
The latest is that the FDA has issued a Refusal-to-File (RTF) letter to Moderna for their mRNA influenza vaccine, mRNA-1010. An RTF means the FDA has determined that the application is so deficient it doesn’t even warrant a review. RTF letters are not unheard of, but they’re rare—especially given that Moderna spent hundreds of millions of dollars running Phase 3 trials enrolling over 43,000 participants based on FDA guidance, and is now being told the (apparently) agreed-upon design was inadequate.
Moderna compared the efficacy of their vaccine to a standard flu vaccine widely used in the United States. The FDA’s stated rationale is that the control arm did not reflect the “best-available standard of care.” In plain English, that appears to mean the comparator should have been one of the ACIP-preferred “enhanced” flu vaccines for adults 65+ (e.g., high-dose/adjuvanted) rather than a standard-dose product.
Out of context, that’s not crazy but it’s also not necessarily wise. There is nothing wrong with having multiple drugs and vaccines, some of which are less effective on average than others. We want a medical armamentarium: different platforms, different supply chains, different side-effect profiles, and more options when one product isn’t available or isn’t a good fit. The mRNA vaccines, for example, can be updated faster than standard vaccines, so having an mRNA option available may produce superior real-world effectiveness even if it were less efficacious in a head-to-head trial.
In context, this looks like the regulatory rules of the game are being changed retroactively—a textbook example of regulatory uncertainty destroying option value. STAT News reports that Vinay Prasad personally handled the letter and overrode staff who were prepared to proceed with review. Moderna took the unusual step of publicly releasing Prasad’s letter—companies almost never do this, suggesting they’ve calculated the reputational risk of publicly fighting the FDA is lower than the cost of acquiescing.
Moreover, the comparator issue was discussed—and seemingly settled—beforehand. Moderna says the FDA agreed with the trial design in April 2024, and as recently as August 2025 suggested it would file the application and address comparator issues during the review process.
Finally, Moderna also provided immunogenicity and safety data from a separate Phase 3 study in adults 65+ comparing mRNA-1010 against a licensed high-dose flu vaccine, just as FDA had requested—yet the application was still refused.
What is most disturbing is not the specifics of this case but the arbitrariness and capriciousness of the process. The EU, Canada, and Australia have all accepted Moderna’s application for review. We may soon see an mRNA flu vaccine available across the developed world but not in the United States—not because it failed on safety or efficacy, but because FDA political leadership decided, after the fact, that the comparator choice they inherited was now unacceptable.
The irony is staggering. Moderna is an American company. Its mRNA platform was developed at record speed with billions in U.S. taxpayer support through Operation Warp Speed — the signature public health achievement of the first Trump administration. The same government that funded the creation of this technology is now dismantling it. In August, HHS canceled $500 million in BARDA contracts for mRNA vaccine development and terminated a separate $590 million contract with Moderna for an avian flu vaccine. Several states have introduced legislation to ban mRNA vaccines. Insanity.
The consequences are already visible. In January, Moderna’s CEO announced the company will no longer invest in new Phase 3 vaccine trials for infectious diseases: “You cannot make a return on investment if you don’t have access to the U.S. market.” Vaccines for Epstein-Barr virus, herpes, and shingles have been shelved. That’s what regulatory roulette buys you: a shrinking pipeline of medical innovation.
An administration that promised medical freedom is delivering medical nationalism: fewer options, less innovation, and a clear signal to every company considering pharmaceutical investment that the rules can change after the game is played. And this isn’t a one-product story. mRNA is a general-purpose platform with spillovers across infectious disease and vaccines for cancer; if the U.S. turns mRNA into a political third rail, the investment, talent, and manufacturing will migrate elsewhere. America built this capability, and we’re now choosing to export it—along with the health benefits.
Immigration and health for elderly Americans
We measure the impact of increased immigration on mortality among elderly Americans, who rely on the immigrant-intensive health and long-term care sectors. Using a shift-share approach we find a strong impact of immigration on the size of the immigrant care workforce: admitting 1,000 new immigrants would lead to 142 new foreign healthcare workers, without evidence of crowd out of native health care workers. We also find striking effects on mortality: a 25% increase in the steady state flow of immigrants to the US would result in 5,000 fewer deaths nationwide. We identify reduced use of nursing homes as a key mechanism driving this result.
That is from a new NBER working paper by
Trump’s Pharmaceutical Plan
Pharmaceuticals have high fixed costs of R&D and low marginal costs. The first pill costs a billion dollars; the second costs 50 cents. That cost structure makes price discrimination—charging different customers different prices based on willingness to pay—common.
Price discrimination is why poorer countries get lower prices. Not because firms are charitable, but because a high price means poorer countries buy nothing, while any price above marginal cost is still profit. This type of price discrimination is good for poorer countries, good for pharma, and (indirectly) good for the United States: more profits mean more R&D and, over time, more drugs.
The political problem, however, is that Americans look abroad, see lower prices for branded drugs, and conclude that they’re being ripped off. Riding that grievance, Trump has demanded that U.S. prices be no higher than the lowest level paid in other developed countries.
One immediate effect is to help pharma in negotiations abroad: they can now credibly say, “We can’t sell to you at that discount, because you’ll export your price back into the U.S.” But two big issues follow.
First, this won’t lower U.S. prices on current drugs. Firms are already profit-maximizing in the U.S. If they manage to raise prices in France, they don’t then announce, “Great news—now we’ll charge less in America.” The potential upside of the Trump plan isn’t lower prices but higher pharma profits, which strengthens incentives to invest in R&D. If profits rise, we may get more drugs in the long run. But try telling the American voter that higher pharma profits are good.
The second issue is that the plan can backfire.
In our textbook, Modern Principles, Tyler and I discuss almost exactly this scenario: suppose policy effectively forces a single price across countries. Which price do firms choose—the low one abroad or the high one in the U.S.? Since a large share of profits comes from the U.S., they’re likely to choose the high price:
Pfizer CEO Albert Bourla was even more direct, saying it is time for countries such as France to pay more or go without new drugs. If forced to choose between reducing U.S. prices to France’s level or stopping supply to France, Pfizer would choose the latter, Bourla told reporters at a pharma-industry conference.
So the real question is: will other countries pay?
If France tried to force Americans to pay more to subsidize French price controls, U.S. voters would explode. Yet that’s essentially what other countries are being told but in reverse: “You must pay more so Americans can pay less.” Other countries are already stingier than the U.S., and they already bear costs for it—new drugs arrive more slowly abroad than here. Some governments may decide—foolishly, but understandably—that paying U.S.-level prices is politically impossible. If so, they won’t “harmonize upward.” They’ll follow the European way: ration, delay and go without.
In that case, nobody wins. Pharma profits fall, R&D declines, U.S. prices don’t magically drop, and patients abroad get fewer new drugs and worse care. Lose-lose-lose.
We don’t know the equilibrium, but lose-lose-lose is entirely plausible. Switzerland, for example, does not seem willing to pay more:
Yet Switzerland has shown little political willingness to pay more—threatening both the availability of medications in the country and its role as a global leader in developing therapies. Drug prices are the primary driver of the increasing cost of mandatory health coverage, and the topic generates heated debate during the annual reappraisal of insurance rates. “The Swiss cannot and must not pay for price reductions in the USA with their health insurance premiums,” says Elisabeth Baume-Schneider, Switzerland’s home affairs minister.
If many countries respond like Switzerland—and Trump’s unpopularity abroad doesn’t help—the sector ends up less profitable and innovation slows. Voters may feel less “ripped off,” but they’ll be buying that feeling with fewer drugs and sicker bodies.